


 CorLab AI Agent

Welcome to your Personal Assistant
This Tech Assistant is designed to support you with clear insights into our company, our work, our services and the people behind our progress.
Powered by CorLab Tech © 2025
Mental Health App Development: Integrations, Compliance, and Build Process
After a video follow-up, a psychiatrist needs three things before the next patient: the current lab result, a renewed prescription, and an open slot for the next visit. If those live in three separate systems, the visit ends in tabs and phone calls. Mental health app development is the work of building software that keeps those steps in one place.
Mental health app development covers the design, engineering, and maintenance of patient apps, telepsychiatry software for clinicians, and back-office tools that handle sessions, records, prescriptions, billing, and privacy-regulated data. A complete build connects to the EHR over HL7 FHIR, takes in device data, reads lab results, syncs with practice management, and places HIPAA-aligned controls, consent handling, and crisis escalation in the architecture from the start.
What does mental health app development include?
Mental health app development includes the discovery, design, engineering, compliance work, integration, testing, and ongoing maintenance of software used in behavioral care. The scope reaches well beyond the app screen. It covers how the software stores sensitive records, exchanges data with clinical systems, supports clinicians during a session, and keeps patients engaged after the first week.
Two things separate this work from general app development. The records are highly sensitive, and the users fall into two very different groups. Patients may open the app while distressed, and clinicians have minutes between sessions. A design that suits one group can fail the other.
The demand is visible in claims data. In the second quarter of 2026, 53.7% of commercially insured patients with a telehealth claim had one for a mental health condition, according to FAIR Health. Drawing on our healthcare software projects, this guide covers the integrations, compliance decisions, and build steps behind that demand.
What types of behavioral health software exist?
Behavioral health software falls into three product types: patient apps, provider platforms, and back-office systems. Patient apps handle self-tracking, messaging, and sessions. Provider platforms handle charting, prescribing, and treatment plans. Back-office systems handle scheduling, billing, and reporting. Real projects usually combine two or three of these around one shared patient record.
A patient app succeeds or fails in its first minutes. Sign-up has to be short, consent has to be clear, and the first session has to be one tap away. Cross-platform support matters because patients switch devices, and speech-to-text and colorblind-friendly modes decide who can use the app at all.
A provider platform is judged by the clinician time it saves. Charting, prescribing, lab review, and treatment plans should sit within a few clicks of the video session. On a telepsychiatry build, the test is simple: can a clinician close one visit and open the next without leaving the platform?
The back office is easy to underestimate. Scheduling rules, insurance billing, and reporting decide whether a practice can actually run on the platform. Building these early, with front-desk staff reviewing them, avoids a common late surprise: a working clinical tool that the front desk cannot use.
How does mental health EHR integration work?
Mental health EHR integration connects an app to a clinic's EHR or EMR so that clinicians work from one patient profile. In the United States, certified EHRs expose patient data through HL7 FHIR, a standard format for health data APIs. The app reads medications, diagnoses, and prior treatments, and writes back session notes and prescriptions where the vendor allows it.
The main engineering decision is read versus write. The Office of the National Coordinator for Health IT certification criterion for standardized APIs covers read services over FHIR R4, so pulling a medication history is well supported. Writing a note or prescription back usually depends on the vendor’s own API or on HL7 v2 messaging.
Mental health adds a second decision: what must not sync by default. Under HIPAA, psychotherapy notes kept apart from the medical record generally need a specific patient authorization before disclosure, according to HHS. Storing those notes separately from progress notes makes that rule enforceable in the schema.
Patient matching is the quiet risk. Two records for one person, or one record for two, cause clinical errors, so the integration needs a matching rule and a review queue for uncertain cases. Prescribing adds its own standards, which our separate article on e-prescribing in Moldova covers in more detail.
Device data integration
A wearable can report heart rate every few seconds, yet a clinician reviewing a sleep complaint needs one trend, not thousands of readings. The engineering decision is where to summarize. Raw readings stay in inexpensive storage, and only daily or weekly summaries enter the clinical record as FHIR Observation resources, the HL7 format for measurements about a patient or device.
Consent has to work per data stream, so a patient can share sleep data and pause heart rate without leaving the app. On healthcare projects, we have seen device data volume, not the app itself, become the bottleneck. That shapes the design early: queue incoming data, cap what each device can send, and monitor ingestion.
A prototype that streams a live heart rate proves the connection works. It does not prove the data is clean enough for a clinician to act on. Devices drop signal and users take wearables off, so summaries should show data completeness next to every number, or a gap will read as a healthy night.
Laboratory information system integration
A prescriber renewing a mood stabilizer wants the current blood test result on the same screen as the refill request. Laboratory information system integration makes that possible. Results usually arrive as HL7 v2 messages or as FHIR DiagnosticReport and Observation resources, and the app should accept both.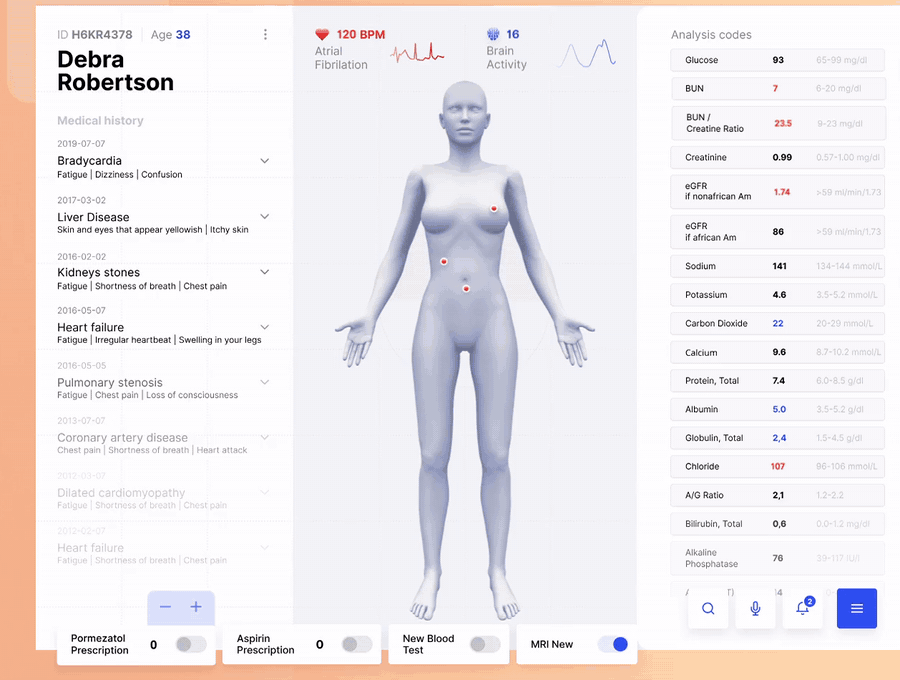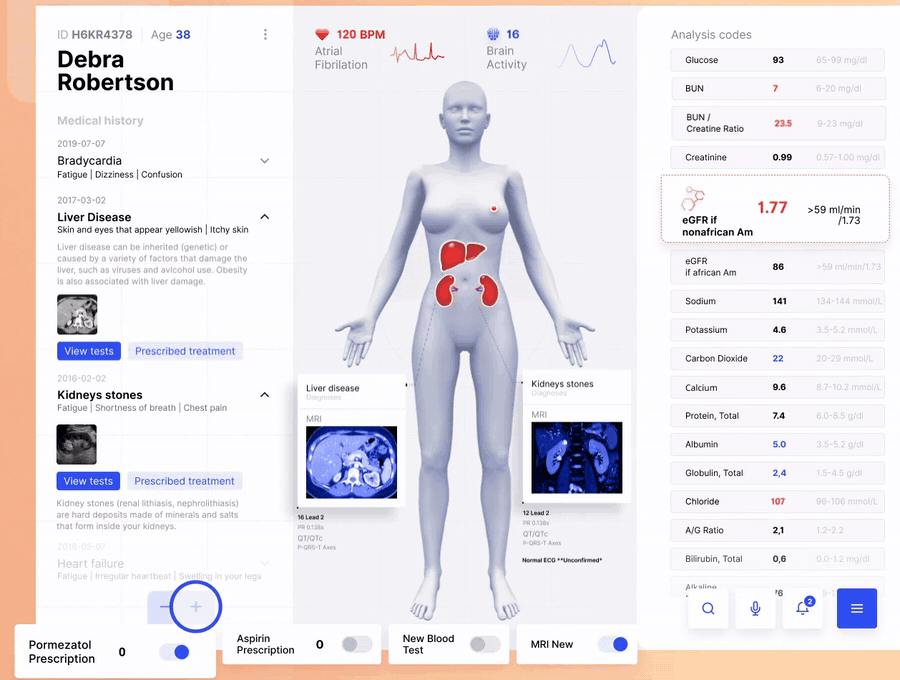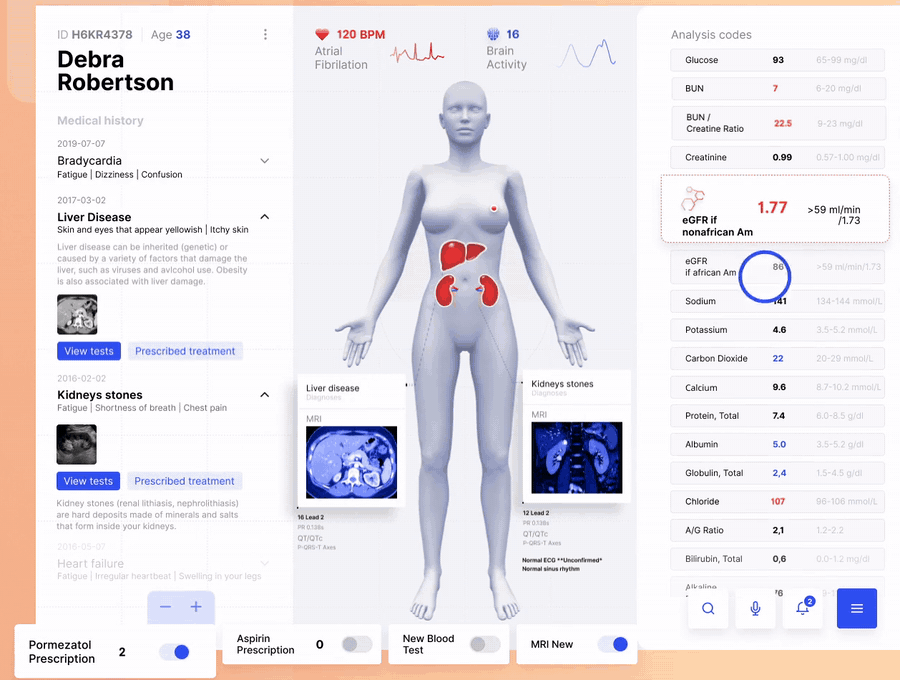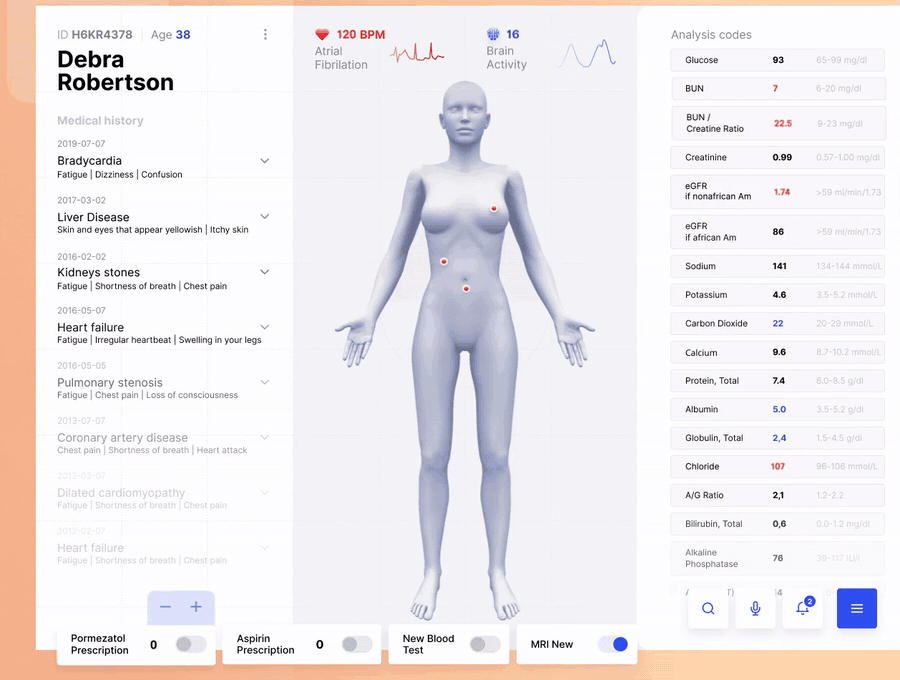
The core decision is code mapping. Each laboratory labels tests with its own local codes, so results need mapping to a standard vocabulary such as LOINC once, in one place. Anything unmapped should land in a review queue for a person to resolve. A silently dropped result is invisible to the clinician.
Show each laboratory's own reference range beside the value, because ranges differ between laboratories. Keep clinical alerting with the laboratory's established process, and let the app display results instead of deciding what they mean. Responsibility for interpretation stays with the clinician, and the interface should make that clear.
Practice management system integration
A video follow-up and an in-person intake can carry different billing codes, and the practice management system decides which applies. Integration keeps scheduling, reminders, billing, and reporting on one appointment record. Without it, the front desk retypes visits into two systems, and the records drift apart.
The main decision is which system owns the schedule. Pick one, usually the practice management system, and have the app read and write appointments through its API rather than keeping a second calendar. Duplicated scheduling logic is where double bookings and missed reminders come from.
Plan for the other system being down. Queue appointment changes, retry them, and show the clinician when a booking has not synced yet. A visit that starts late because a slot did not sync costs the patient time and trust, and the fix belongs in the design.
Where do HIPAA alignment, consent, and crisis escalation enter the build?
HIPAA alignment, consent, and crisis escalation enter a mental health app build at architecture design, not at final review. Data models, access controls, audit logging, and escalation rules are structural choices that are costly to retrofit. Compliance work that starts at testing usually becomes a rewrite.
The HHS Office for Civil Rights explains in its health app guidance when an app developer may count as a business associate: when it handles protected health information on behalf of a covered entity such as a clinic. In practice, that means encryption, role-based access, audit logs, and a signed business associate agreement before real patient data enters any environment.
HHS also states that it does not certify any person or product as HIPAA compliant, so the accurate description of software is HIPAA-aligned or built to HIPAA requirements. Any mental health app development company you evaluate should show where consent is stored, how escalation alerts are tested, and how its business associate agreement works.
Consent is a data model question, not a checkbox. The app has to record what the patient agreed to, when, and for which use, and to honor a withdrawal without erasing clinical history the provider must keep. Versioning the consent text lets a later audit show which wording the patient saw.
Substance use disorder (SUD) records add another layer. The federal rule 42 CFR Part 2 covers federally assisted SUD programs, and its 2024 update had a compliance date of February 16, 2026. HHS states that segmenting these records is not required, but it requires separate consent for SUD counseling notes. An app can keep one clinical record if it can tag Part 2 data and attach the right consent.
Crisis escalation logic needs a clinical owner as well as an engineer. Decide which inputs raise a flag, such as a screening score or a message, who is notified, how fast, and what the patient sees while waiting. Show emergency contacts that match the patient's country, and test every path with realistic scenarios before launch.
No automated rule catches every crisis, and the software should never present itself as a replacement for emergency care. Every escalation path should end with a human, and every alert should be logged. The goal is a system that fails visibly, so a missed flag is caught by a person instead of by chance.
How does the mental health app build process work?
A mental health app build runs in nine steps, from stakeholder research through launch, training, and ongoing maintenance. Each step should end with something a clinician can review, such as a workflow map, a prototype, or a test report. That keeps clinical judgment inside the project from the first week instead of leaving it for the final review. Startups testing a new care model usually run a shorter version of these steps first, which is how we approach MVP development for startups.
We follow the sequence below on healthcare builds, and the order matters more than the labels. Compliance sits at step five, but its inputs start in step one, and integration testing overlaps with development rather than waiting until it ends. Steps also overlap, so the clinician review at the end of each one keeps the work on track.
1. Understand the needs
Start with interviews across clinicians, front-desk staff, and patients. Ask what breaks in current tools and which workarounds people use. The output is a list of workflows ranked by pain, not a feature list, because a tool that mirrors a real workflow needs fewer features than one built from a wish list.
2. Design features and select technology
Choose features from the ranked workflows: secure messaging, video sessions, progress tracking, and scheduling. Then pick a stack against three constraints: performance on weak mobile connections, support for the required integrations, and a team that can maintain it. Write down the trade-offs so a later team can see why.
3. Plan the project
Turn the scope into milestones, owners, and a budget. Put each integration on the plan as its own line item, since vendor access and sandbox testing follow the vendor's calendar. Agree early on what done means for a clinical feature, because working in a demo is not the same as recording care.
4. Craft an intuitive user experience
Design for two audiences and test with both. Patients need short flows, plain language, and accessibility options. Clinicians need dense screens that keep the video call, chart, and notes in view. Run early prototypes with real users and change the design before any code hardens around it.
5. Build with compliance in mind
Treat privacy and security as build requirements from the first sprint: encryption in transit and at rest, role-based access, audit logs, and consent records. Sign the business associate agreement before real patient data enters any environment. Reviewing compliance only at the end tends to reopen decisions about the data model.
6. Integrate with health tools
Connect the EHR, lab system, practice management system, and device sources one at a time, starting with the one clinicians rely on daily. For each, agree on the data contract and on what happens when the other system is down. Wearables and EEG headsets come last because their formats vary widely.
7. Test thoroughly
Test three layers: functional behavior, integration behavior, and clinical safety. Run realistic scenarios, including a dropped video call mid-session, a duplicate patient record, and a crisis flag raised at night. Involve clinicians as testers. Passing a test script is different from working in a real clinic.
8. Launch and train users
Release to a small group of clinicians first, then widen access. Provide onboarding for clinicians, front-desk staff, and patients, since each group meets a different part of the product. Watch where users stall during the first weeks, because those points show which screens need work.
9. Maintain and evolve
Plan for continuing work: security patches, operating system updates, vendor API changes, and new regulation. The Part 2 compliance date of February 16, 2026 is a recent example of a rule change that can require changes to consent handling. Review usage data monthly and retire features nobody uses.
Why is retention the hard problem in mental health apps?
Retention is the hard problem in mental health apps because the majority of installs never become sustained use. A Journal of Medical Internet Research analysis of popular apps found a median 15-day retention of 3.9% and 30-day retention of 3.3%. Plan retention as a design requirement from the first release, not a marketing task for later.
The study covered 93 popular consumer apps on Google Play, so a platform prescribed by a clinic faces different conditions. A clinician who expects the patient to show up may lift retention, but the study cannot say by how much. Some low retention also reflects tools that did their job quickly, so treat the figures as a warning, not a forecast.
The practical response is to tie the app to the care plan. Appointment and homework reminders, short check-ins, visible progress toward treatment goals, and secure messaging with a clinician give patients a reason to return that someone else also cares about. Badges can add motivation if they never turn a clinical goal into a game score.
Measure retention from the first release. Track how many patients are active on day 1, day 7, and day 30, and treat each drop as a defect to investigate with users. A retention curve that clinicians can see also shows which patients may need a call before they disappear.
After a video follow-up, a psychiatrist needs three things before the next patient: the current lab result, a renewed prescription, and an open slot for the next visit. If those live in three separate systems, the visit ends in tabs and phone calls. Mental health app development is the work of building software that keeps those steps in one place.
Mental health app development covers the design, engineering, and maintenance of patient apps, telepsychiatry software for clinicians, and back-office tools that handle sessions, records, prescriptions, billing, and privacy-regulated data. A complete build connects to the EHR over HL7 FHIR, takes in device data, reads lab results, syncs with practice management, and places HIPAA-aligned controls, consent handling, and crisis escalation in the architecture from the start.
What does mental health app development include?
Mental health app development includes the discovery, design, engineering, compliance work, integration, testing, and ongoing maintenance of software used in behavioral care. The scope reaches well beyond the app screen. It covers how the software stores sensitive records, exchanges data with clinical systems, supports clinicians during a session, and keeps patients engaged after the first week.
Two things separate this work from general app development. The records are highly sensitive, and the users fall into two very different groups. Patients may open the app while distressed, and clinicians have minutes between sessions. A design that suits one group can fail the other.
The demand is visible in claims data. In the second quarter of 2026, 53.7% of commercially insured patients with a telehealth claim had one for a mental health condition, according to FAIR Health. Drawing on our healthcare software projects, this guide covers the integrations, compliance decisions, and build steps behind that demand.
What types of behavioral health software exist?
Behavioral health software falls into three product types: patient apps, provider platforms, and back-office systems. Patient apps handle self-tracking, messaging, and sessions. Provider platforms handle charting, prescribing, and treatment plans. Back-office systems handle scheduling, billing, and reporting. Real projects usually combine two or three of these around one shared patient record.
A patient app succeeds or fails in its first minutes. Sign-up has to be short, consent has to be clear, and the first session has to be one tap away. Cross-platform support matters because patients switch devices, and speech-to-text and colorblind-friendly modes decide who can use the app at all.
A provider platform is judged by the clinician time it saves. Charting, prescribing, lab review, and treatment plans should sit within a few clicks of the video session. On a telepsychiatry build, the test is simple: can a clinician close one visit and open the next without leaving the platform?
The back office is easy to underestimate. Scheduling rules, insurance billing, and reporting decide whether a practice can actually run on the platform. Building these early, with front-desk staff reviewing them, avoids a common late surprise: a working clinical tool that the front desk cannot use.
How does mental health EHR integration work?
Mental health EHR integration connects an app to a clinic's EHR or EMR so that clinicians work from one patient profile. In the United States, certified EHRs expose patient data through HL7 FHIR, a standard format for health data APIs. The app reads medications, diagnoses, and prior treatments, and writes back session notes and prescriptions where the vendor allows it.
The main engineering decision is read versus write. The Office of the National Coordinator for Health IT certification criterion for standardized APIs covers read services over FHIR R4, so pulling a medication history is well supported. Writing a note or prescription back usually depends on the vendor’s own API or on HL7 v2 messaging.
Mental health adds a second decision: what must not sync by default. Under HIPAA, psychotherapy notes kept apart from the medical record generally need a specific patient authorization before disclosure, according to HHS. Storing those notes separately from progress notes makes that rule enforceable in the schema.
Patient matching is the quiet risk. Two records for one person, or one record for two, cause clinical errors, so the integration needs a matching rule and a review queue for uncertain cases. Prescribing adds its own standards, which our separate article on e-prescribing in Moldova covers in more detail.
Device data integration
A wearable can report heart rate every few seconds, yet a clinician reviewing a sleep complaint needs one trend, not thousands of readings. The engineering decision is where to summarize. Raw readings stay in inexpensive storage, and only daily or weekly summaries enter the clinical record as FHIR Observation resources, the HL7 format for measurements about a patient or device.
Consent has to work per data stream, so a patient can share sleep data and pause heart rate without leaving the app. On healthcare projects, we have seen device data volume, not the app itself, become the bottleneck. That shapes the design early: queue incoming data, cap what each device can send, and monitor ingestion.
A prototype that streams a live heart rate proves the connection works. It does not prove the data is clean enough for a clinician to act on. Devices drop signal and users take wearables off, so summaries should show data completeness next to every number, or a gap will read as a healthy night.
Laboratory information system integration
A prescriber renewing a mood stabilizer wants the current blood test result on the same screen as the refill request. Laboratory information system integration makes that possible. Results usually arrive as HL7 v2 messages or as FHIR DiagnosticReport and Observation resources, and the app should accept both.
The core decision is code mapping. Each laboratory labels tests with its own local codes, so results need mapping to a standard vocabulary such as LOINC once, in one place. Anything unmapped should land in a review queue for a person to resolve. A silently dropped result is invisible to the clinician.
Show each laboratory's own reference range beside the value, because ranges differ between laboratories. Keep clinical alerting with the laboratory's established process, and let the app display results instead of deciding what they mean. Responsibility for interpretation stays with the clinician, and the interface should make that clear.
Practice management system integration
A video follow-up and an in-person intake can carry different billing codes, and the practice management system decides which applies. Integration keeps scheduling, reminders, billing, and reporting on one appointment record. Without it, the front desk retypes visits into two systems, and the records drift apart.
The main decision is which system owns the schedule. Pick one, usually the practice management system, and have the app read and write appointments through its API rather than keeping a second calendar. Duplicated scheduling logic is where double bookings and missed reminders come from.
Plan for the other system being down. Queue appointment changes, retry them, and show the clinician when a booking has not synced yet. A visit that starts late because a slot did not sync costs the patient time and trust, and the fix belongs in the design.
Where do HIPAA alignment, consent, and crisis escalation enter the build?
HIPAA alignment, consent, and crisis escalation enter a mental health app build at architecture design, not at final review. Data models, access controls, audit logging, and escalation rules are structural choices that are costly to retrofit. Compliance work that starts at testing usually becomes a rewrite.
The HHS Office for Civil Rights explains in its health app guidance when an app developer may count as a business associate: when it handles protected health information on behalf of a covered entity such as a clinic. In practice, that means encryption, role-based access, audit logs, and a signed business associate agreement before real patient data enters any environment.
HHS also states that it does not certify any person or product as HIPAA compliant, so the accurate description of software is HIPAA-aligned or built to HIPAA requirements. Any mental health app development company you evaluate should show where consent is stored, how escalation alerts are tested, and how its business associate agreement works.
Consent is a data model question, not a checkbox. The app has to record what the patient agreed to, when, and for which use, and to honor a withdrawal without erasing clinical history the provider must keep. Versioning the consent text lets a later audit show which wording the patient saw.
Substance use disorder (SUD) records add another layer. The federal rule 42 CFR Part 2 covers federally assisted SUD programs, and its 2024 update had a compliance date of February 16, 2026. HHS states that segmenting these records is not required, but it requires separate consent for SUD counseling notes. An app can keep one clinical record if it can tag Part 2 data and attach the right consent.
Crisis escalation logic needs a clinical owner as well as an engineer. Decide which inputs raise a flag, such as a screening score or a message, who is notified, how fast, and what the patient sees while waiting. Show emergency contacts that match the patient's country, and test every path with realistic scenarios before launch.
No automated rule catches every crisis, and the software should never present itself as a replacement for emergency care. Every escalation path should end with a human, and every alert should be logged. The goal is a system that fails visibly, so a missed flag is caught by a person instead of by chance.
How does the mental health app build process work?
A mental health app build runs in nine steps, from stakeholder research through launch, training, and ongoing maintenance. Each step should end with something a clinician can review, such as a workflow map, a prototype, or a test report. That keeps clinical judgment inside the project from the first week instead of leaving it for the final review. Startups testing a new care model usually run a shorter version of these steps first, which is how we approach MVP development for startups.
We follow the sequence below on healthcare builds, and the order matters more than the labels. Compliance sits at step five, but its inputs start in step one, and integration testing overlaps with development rather than waiting until it ends. Steps also overlap, so the clinician review at the end of each one keeps the work on track.
1. Understand the needs
Start with interviews across clinicians, front-desk staff, and patients. Ask what breaks in current tools and which workarounds people use. The output is a list of workflows ranked by pain, not a feature list, because a tool that mirrors a real workflow needs fewer features than one built from a wish list.
2. Design features and select technology
Choose features from the ranked workflows: secure messaging, video sessions, progress tracking, and scheduling. Then pick a stack against three constraints: performance on weak mobile connections, support for the required integrations, and a team that can maintain it. Write down the trade-offs so a later team can see why.
3. Plan the project
Turn the scope into milestones, owners, and a budget. Put each integration on the plan as its own line item, since vendor access and sandbox testing follow the vendor's calendar. Agree early on what done means for a clinical feature, because working in a demo is not the same as recording care.
4. Craft an intuitive user experience
Design for two audiences and test with both. Patients need short flows, plain language, and accessibility options. Clinicians need dense screens that keep the video call, chart, and notes in view. Run early prototypes with real users and change the design before any code hardens around it.
5. Build with compliance in mind
Treat privacy and security as build requirements from the first sprint: encryption in transit and at rest, role-based access, audit logs, and consent records. Sign the business associate agreement before real patient data enters any environment. Reviewing compliance only at the end tends to reopen decisions about the data model.
6. Integrate with health tools
Connect the EHR, lab system, practice management system, and device sources one at a time, starting with the one clinicians rely on daily. For each, agree on the data contract and on what happens when the other system is down. Wearables and EEG headsets come last because their formats vary widely.
7. Test thoroughly
Test three layers: functional behavior, integration behavior, and clinical safety. Run realistic scenarios, including a dropped video call mid-session, a duplicate patient record, and a crisis flag raised at night. Involve clinicians as testers. Passing a test script is different from working in a real clinic.
8. Launch and train users
Release to a small group of clinicians first, then widen access. Provide onboarding for clinicians, front-desk staff, and patients, since each group meets a different part of the product. Watch where users stall during the first weeks, because those points show which screens need work.
9. Maintain and evolve
Plan for continuing work: security patches, operating system updates, vendor API changes, and new regulation. The Part 2 compliance date of February 16, 2026 is a recent example of a rule change that can require changes to consent handling. Review usage data monthly and retire features nobody uses.
Why is retention the hard problem in mental health apps?
Retention is the hard problem in mental health apps because the majority of installs never become sustained use. A Journal of Medical Internet Research analysis of popular apps found a median 15-day retention of 3.9% and 30-day retention of 3.3%. Plan retention as a design requirement from the first release, not a marketing task for later.
The study covered 93 popular consumer apps on Google Play, so a platform prescribed by a clinic faces different conditions. A clinician who expects the patient to show up may lift retention, but the study cannot say by how much. Some low retention also reflects tools that did their job quickly, so treat the figures as a warning, not a forecast.
The practical response is to tie the app to the care plan. Appointment and homework reminders, short check-ins, visible progress toward treatment goals, and secure messaging with a clinician give patients a reason to return that someone else also cares about. Badges can add motivation if they never turn a clinical goal into a game score.
Measure retention from the first release. Track how many patients are active on day 1, day 7, and day 30, and treat each drop as a defect to investigate with users. A retention curve that clinicians can see also shows which patients may need a call before they disappear.
Frequently Asked Questions

How much does mental health app development cost?
Mental health app development cost depends on scope: platforms supported, features, the number of integrations, and compliance work. Our average hourly rate is $25 to $49, so a total follows from the hours each part needs. Each integration, such as the EHR, laboratory system, device data, and practice management, should be estimated as its own line item.

How long does it take to build a mental health app?
What HIPAA obligations apply to mental health app data?
How should a mental health app integrate with an EHR?
What is the difference between telepsychiatry software and a telehealth platform?
Which features drive retention in a mental health app?
Should a team build a custom mental health app or use a white-label platform?

Author
With more than 10 years in full-stack development and real-world experience in healthcare, I bring a unique blend of technical skills and domain knowledge to every project. My focus is on building solutions that solve real problems and support better outcomes.
I often bring AI into the mix to enhance performance and simplify the complex. It’s all about creating smarter tools that help people work more efficiently and make better decisions.


Our Best Insights
Browse More Articles
Want to know what’s trending in the tech world? Our articles break it all down - quickly and clearly.
 Time to read: 11 min

Healthcare

Artificial Intelligence
November 4th, 2024
Machine Learning in Healthcare: Benefits, Use Cases, and Limits
Where machine learning helps in healthcare, why so many projects stall after the pilot, and when a simple rule beats a model.

 Time to read: 5 min
Healthcare
October 3rd, 2024
Digital Transformation in Healthcare: What It Means in Software Terms
From clinics to enterprise systems, digital transformation is making healthcare software more accessible, efficient, and patient-focused.


Thinking about building your own app?
Let's make it happen! Dream big, build smart - we’ll take care of the tech.
 Get a free consultation