




 CorLab AI Agent

Welcome to your Personal Assistant
This Tech Assistant is designed to support you with clear insights into our company, our work, our services and the people behind our progress.
Powered by CorLab Tech © 2025
Machine Learning in Healthcare: Benefits, Use Cases, and Limits
Machine learning in healthcare is the use of algorithms that learn patterns from clinical and operational data, such as images, lab results, and admission records, to support decisions instead of following hand-written rules. Its main benefits are faster, more consistent reading of medical images, earlier warning of deterioration, and better forecasts of patient demand.
Those benefits are real but uneven. They depend on clean data, integration into the clinical workflow, and monitoring after launch, and for many problems a simple rule works better than a model. This guide covers where machine learning earns its place in healthcare, why deployments fail, and how to start a project on clinical data.
What are the benefits of machine learning in healthcare?
The benefits of machine learning in healthcare concentrate in two areas: diagnosis support in medical imaging and operational prediction. Operational prediction covers admissions, no-shows, staffing needs, and early warning of deterioration. Machine learning is important in healthcare because data volumes outgrow what people can review by hand, although gains outside these two areas are less proven.
Diagnosis support in medical imaging
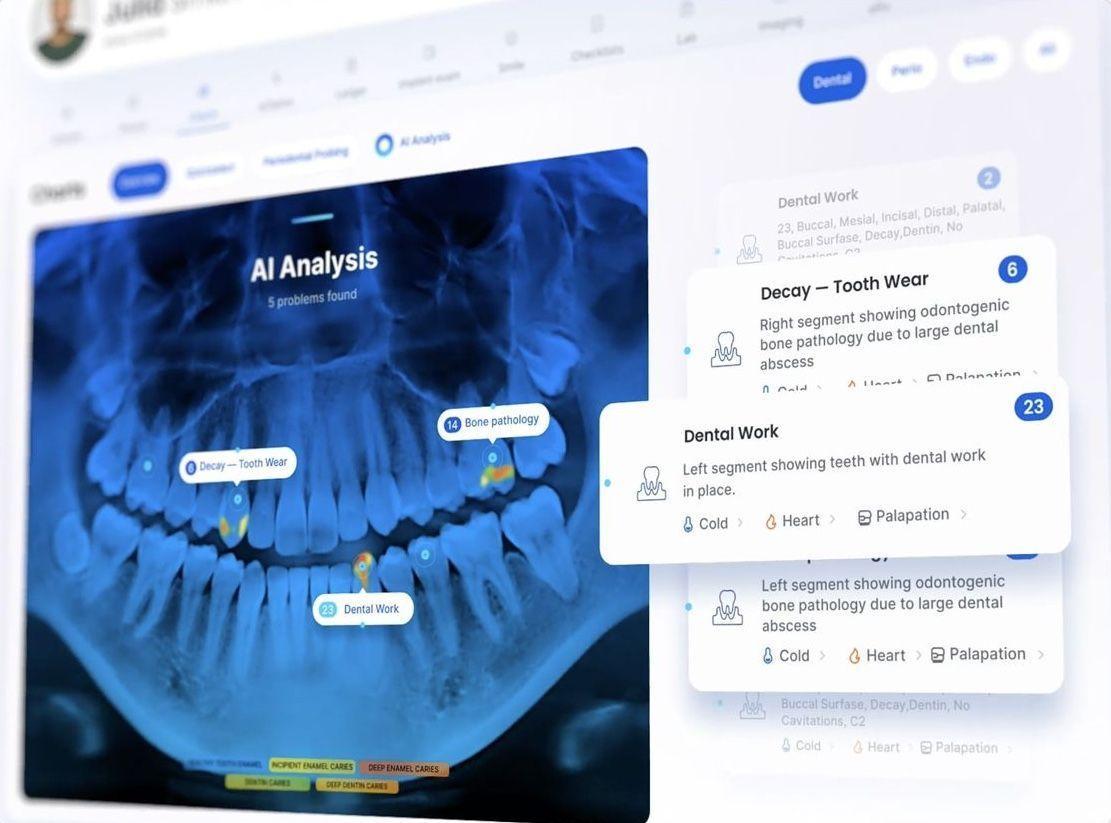
Imaging is where machine learning has a regulatory track record. A 2026 study in the Journal of Medical Internet Research counted 1,430 devices on the FDA's list of AI-enabled medical devices with decisions through 2025, and radiology accounts for most of them. Typical functions include triaging suspected vessel occlusions on CT and prioritizing mammograms for review.
These tools mostly support a reading rather than replace it. A radiologist still makes the call, and the software changes the order or the speed of the work: urgent studies rise to the top of the worklist, and subtle findings get a second look. That framing matters for evaluation, because the right measure is time to treatment or missed findings, not accuracy alone. Speed is often the real benefit.
Outside radiology, machine learning reads ECG traces, pathology slides, and retinal photographs, where the input is a signal or an image and the output is a finding a specialist confirms. Machine learning in medicine fits this kind of narrow, well-labeled perceptual task.
FDA clearance shows that a device is safe and effective for its stated use. It does not show that a particular hospital will see a measurable benefit. Local results depend on the patient mix, the scanners, and how the output fits the reading workflow, so a pilot should measure the local effect before a wider rollout.
Operational prediction
Operational models forecast the events that shape how a hospital runs: which patients will miss appointments, how many beds will be free tomorrow, which shifts will be short-staffed. Errors here cost money and time rather than a diagnosis. That makes the risk easier to manage and the payback easier to measure.
How machine learning helps in healthcare operations is mostly a matter of lead time. A no-show forecast a week ahead lets schedulers send reminders or overbook carefully, and a bed forecast for tomorrow lets managers plan discharges tonight. The value comes from the action the forecast enables, so every operational model needs an owner for that action.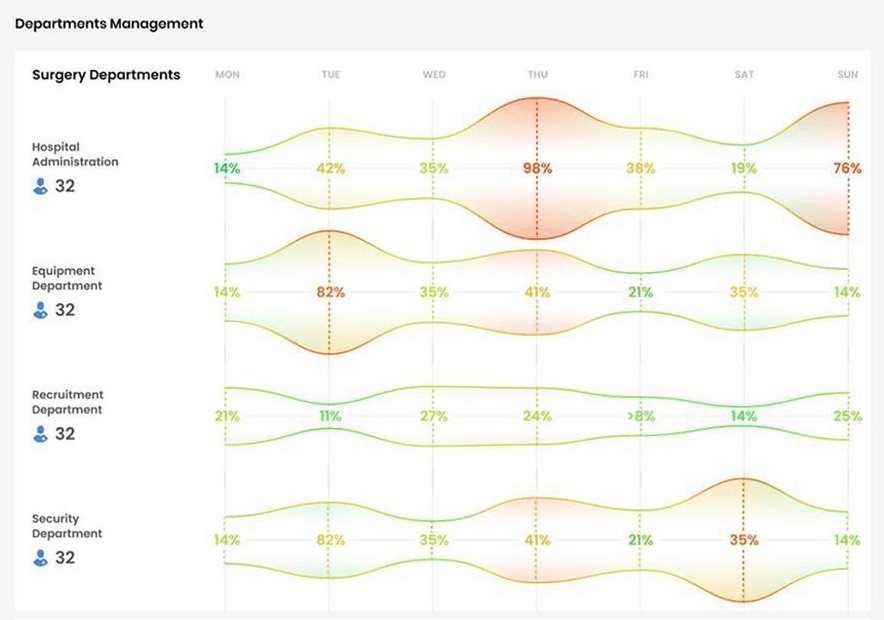
Early-warning scores sit between diagnosis and operations. They watch vital signs and lab results for patterns that often precede deterioration or sepsis and alert the care team. They can buy time for treatment, and they can also flood a ward with false alarms.
Clinicians also report time savings from AI tools more broadly. The Philips Future Health Index 2026 surveyed over 2,000 healthcare professionals in 10 countries. They report savings equivalent to 16 working days a year, while 70 percent say AI training is inadequate, inconsistent, or unavailable. These are self-reported figures from a company that sells AI-enabled equipment.
Research and other uses
Machine learning also supports drug discovery, patient recruitment for clinical trials, and analysis of data from wearables and apps collected with consent. These uses are real, but most sit in research settings rather than daily care, and a hospital buyer will find the evidence for them harder to evaluate.
Generative models, such as large language models that draft notes or summarize records, are a separate branch with their own failure modes, including confident answers that are wrong. This guide focuses on predictive machine learning, where a model outputs a score, a class, or a forecast that can be checked against what actually happened.
Market forecasts are louder than the evidence. A forecast by Arizton, last updated in December 2025, projects that the healthcare AI market will grow from $14.33 billion in 2023 to $153.61 billion by 2029, a 48.50 percent annual rate. A market projection says little about which tools work in a given hospital, so this guide leans on regulatory records and clinical studies.
Why do machine learning projects in healthcare fail after the pilot?
Machine learning projects in healthcare often fail after the pilot because of the data and the workflow, not the algorithm. Training data rarely matches live data, and models sit outside the EHR where clinicians work. Performance drifts as practice changes, and clinicians distrust outputs they cannot explain.
Data quality
Clinical data is recorded for care and billing, not for training models. Diagnosis codes reflect what was billed, timestamps reflect when someone typed, and a missing value often means a test was never ordered. A model trained on this data learns those habits along with the medicine, and it can look accurate for the wrong reasons.
Cleaning takes most of the effort. Labels need clinical review, units need normalizing, and the moment a prediction would have been made has to be reconstructed, so the model never sees information from the future. Skipping that step produces fragile results.
Representativeness is the other data problem. A model trained on one hospital's population can underperform for groups that were rare in its training data, such as younger patients in a dataset dominated by older ones. Reporting performance separately for each major subgroup, before launch, shows whether that gap exists and how large it is. A gap found before launch is a design problem; after launch, it is an incident.
EHR integration
Access to digital records is no longer the barrier it was. The Office of the National Coordinator for Health IT reports that more than 99 percent of non-federal acute care hospitals had adopted a certified EHR as of 2024. Having data in an EHR does not make it usable for a model, and getting predictions back to the clinician is harder still.
A model that lives in a separate dashboard is a model nobody checks during a busy shift. Integration means reading inputs through the EHR's interfaces, such as HL7 FHIR, writing results back where clinicians already look, and agreeing who acts on an alert. That last part is a workflow decision, and it needs clinicians in the room. Routing an alert to the wrong role helps nobody.
Model drift
Models degrade as practice, populations, and coding change, and they often perform worse at a new site. One example is an external validation of a widely used sepsis model by the University of Michigan Medical School. It found an area under the curve of 0.63. Two-thirds of sepsis cases, 67 percent, went unflagged. The vendor disputed the configuration.
The lesson stands either way: vendor figures need local validation, and monitoring has to continue after launch. Performance should be tracked on recent data, alert rates watched for sudden shifts, and retraining handled like any other release, with tests and sign-off. For regulated devices, the FDA's final guidance on predetermined change control plans, issued in December 2024, lets manufacturers get planned model updates authorized in advance.
Alert volume is part of that validation. In the Michigan study, the model alerted on nearly one in five hospitalized patients, a volume that trains staff to click past warnings. Thresholds, suppression rules, and routing to the right role decide whether an accurate model changes care or becomes background noise on the ward. Alert design deserves as much review as the model.
Explainability
Clinicians act on outputs they can check. A score with no reasons attached asks for trust the model has not earned, while a short list of the factors behind a prediction gives the clinician something to verify. Explanations do not make a model correct, but they make its mistakes easier to catch.
Documentation helps as much as explanation. A model card that states the training data, the time period, the intended use, and the known failure cases lets a clinical committee decide where the model applies. It also gives the next team a record to work from when the model is retrained or retired, and a starting point for debugging when performance drops. Keep it next to the code.
When is machine learning the wrong tool in healthcare?
Machine learning is the wrong tool in healthcare when the correct answer can be written as a rule or looked up in a reference. Dose limits, drug interactions, and eligibility criteria are examples. A rules-based system handles them more cheaply, validates more easily, and explains every output, while a model only adds uncertainty.
In the clinical workspaces we build, lab results are shown against their reference ranges. Comparing a value with a range is a rule, not a model, and it should stay one. A clinician reading a potassium result needs the same answer every time, applied by the same logic, not a probability. Rules like this are also simple to audit and explain.
On the medical AI agent I built in three days, drug-to-drug interactions went into a Neo4j knowledge graph instead of being left to the model. An interaction question became a query against that graph, and the language model handled the conversation around it. I had to test and adjust prompts even then, and the facts still came from the graph.
A useful test comes before any project. If a clinician can write the logic on one page, write it as rules and version them. Machine learning earns its place when the pattern is real but too complex to write down, such as reading an image. It also fits when the answer depends on many weak signals, such as predicting which patients will miss an appointment.
Many good systems combine both approaches. Rules handle the hard limits, such as a maximum dose, and a model ranks or prioritizes within them, such as which alerts a pharmacist reviews first. Keeping the rule layer separate also means the safety-critical part never changes when the model is retrained. It also makes validation simpler, because each layer can be tested on its own.
How do you start a machine learning project on clinical data?
A machine learning project on clinical data starts with one decision to improve and one measure of success, not with a dataset. The team then checks whether a rule already solves the problem, secures de-identified data, and validates the model retrospectively before any clinician sees a prediction.
Define the decision first. "Predict readmissions" is a topic; "decide which discharged patients get a follow-up call within 48 hours" is a decision. That framing tells the team what data exists at the moment of decision, who acts on the output, and how success will be measured, such as follow-up calls reaching patients who would otherwise have returned. It also rules out data that arrives too late to use.
Build a rule baseline before the model. A simple scoring rule, written with clinicians, gives the model something to beat. If the model cannot beat it by a margin that matters clinically, the rule ships instead, and the project still delivers a result.
Data access comes next. As the HHS Office for Civil Rights explains, HIPAA allows two de-identification methods: Safe Harbor, which removes 18 specified identifiers, and Expert Determination, where a qualified expert finds the re-identification risk very small. Training on identifiable data instead requires a permitted use and, for vendors, a business associate agreement. Either route should be documented before training starts. Keep any re-identification key outside the training environment.
Validate before anyone relies on the model. Test it on data from a later period than it was trained on, and on a second site where possible. A model that works on last year's patients at one hospital may not work on next year's at another. Then run it silently in production. Log each prediction without showing it, and compare the log with what actually happened.
Only then should a prediction reach the screen, with a named owner for acting on it and a plan for monitoring. Most of the calendar goes to data work and validation, not to model training. The wider shift this fits into is covered in the article on digital transformation in healthcare software development, and applied AI work is on the artificial intelligence page.
The team matters as much as the data. A healthcare machine learning project needs a clinician who owns the decision, a data engineer who knows the EHR, and someone accountable for privacy, alongside the people who build the model. Without the clinical owner, projects tend to optimize a metric that nobody on the ward uses. That owner also decides when the model should be switched off.
Scope creep is the quiet risk. A project that starts with one decision often grows into five, each with its own data and owners. Ship the first model and monitor it for a few months before adding the next. That way the lessons from one decision flow into the next, instead of the same data work being repeated five times in parallel.
Frequently asked questions


What does machine learning in healthcare mean?
Machine learning in healthcare is the use of algorithms that learn patterns from clinical and operational data to support decisions such as diagnosis, risk prediction, and scheduling. Unlike rules-based software, a model learns its logic from examples. Machine learning supports clinicians rather than replacing their judgment.


What are the main benefits of machine learning in healthcare?
What are real examples of machine learning in healthcare?
What data does a healthcare machine learning project need?
What does HIPAA mean for training models on patient data?
Is machine learning better than a rules-based system?
What drives the cost of a healthcare machine learning project?


Author
With more than 10 years in full-stack development and real-world experience in healthcare, I bring a unique blend of technical skills and domain knowledge to every project. My focus is on building solutions that solve real problems and support better outcomes.
I often bring AI into the mix to enhance performance and simplify the complex. It’s all about creating smarter tools that help people work more efficiently and make better decisions.


Thinking about building your own app?
Let's make it happen! Dream big, build smart - we’ll take care of the tech.
 Get a free consultation
Our Best Insights
Browse More Articles
Want to know what’s trending in the tech world? Our articles break it all down - quickly and clearly.
 Time to read: 11 min


Healthcare
March 12th, 2025
E-Prescribing Systems: How They Work, and What a National Rollout Involves
The growing adoption of E-prescribing in Moldova points to a larger trend toward smarter, more connected digital healthcare systems.


 Time to read: 5 min
Healthcare
October 3rd, 2024
Digital Transformation in Healthcare: What It Means in Software Terms
From clinics to enterprise systems, digital transformation is making healthcare software more accessible, efficient, and patient-focused.
We would like to load Google Tag Manager, which brings Google Analytics and a Google Ads audience tag with it, and Microsoft Clarity, which records how pages are used (clicks, scrolling, mouse movement) so that we can see where the site is hard to use. None of that is needed for the site to work, so it only loads if you agree, and you can change your mind at any time from the footer. Separately, Cloudflare measures this site's own performance without cookies and without identifying you; that runs either way and is explained in our Privacy Policy.