





 CorLab AI Agent

Welcome to your Personal Assistant
This Tech Assistant is designed to support you with clear insights into our company, our work, our services and the people behind our progress.
Powered by CorLab Tech © 2025
IoT in Healthcare: Applications, Examples, and Architecture

At 7:40 a.m., a patient with heart failure steps onto a connected scale at home. The reading travels over Bluetooth to a phone acting as the gateway, then to the clinic dashboard, where a weight-gain alert reaches a nurse by 8:00. IoT in healthcare is that chain, from the device that measures to the person who acts.
In full, IoT in healthcare, or the internet of things in healthcare, means connected medical devices and sensors that send health data to clinical systems. Gateways and software platforms carry it between them. Its main uses are remote patient monitoring, hospital asset tracking, medication adherence, and wearable health data. What it delivers depends less on the device than on the data architecture behind each reading.
How does IoT in healthcare work?
IoT in healthcare works by moving a reading through four layers, from device and gateway to data platform and the clinician who acts on it. Each layer can fail on its own, so each needs its own rules for validation and security. Most of the engineering work sits in the two middle layers.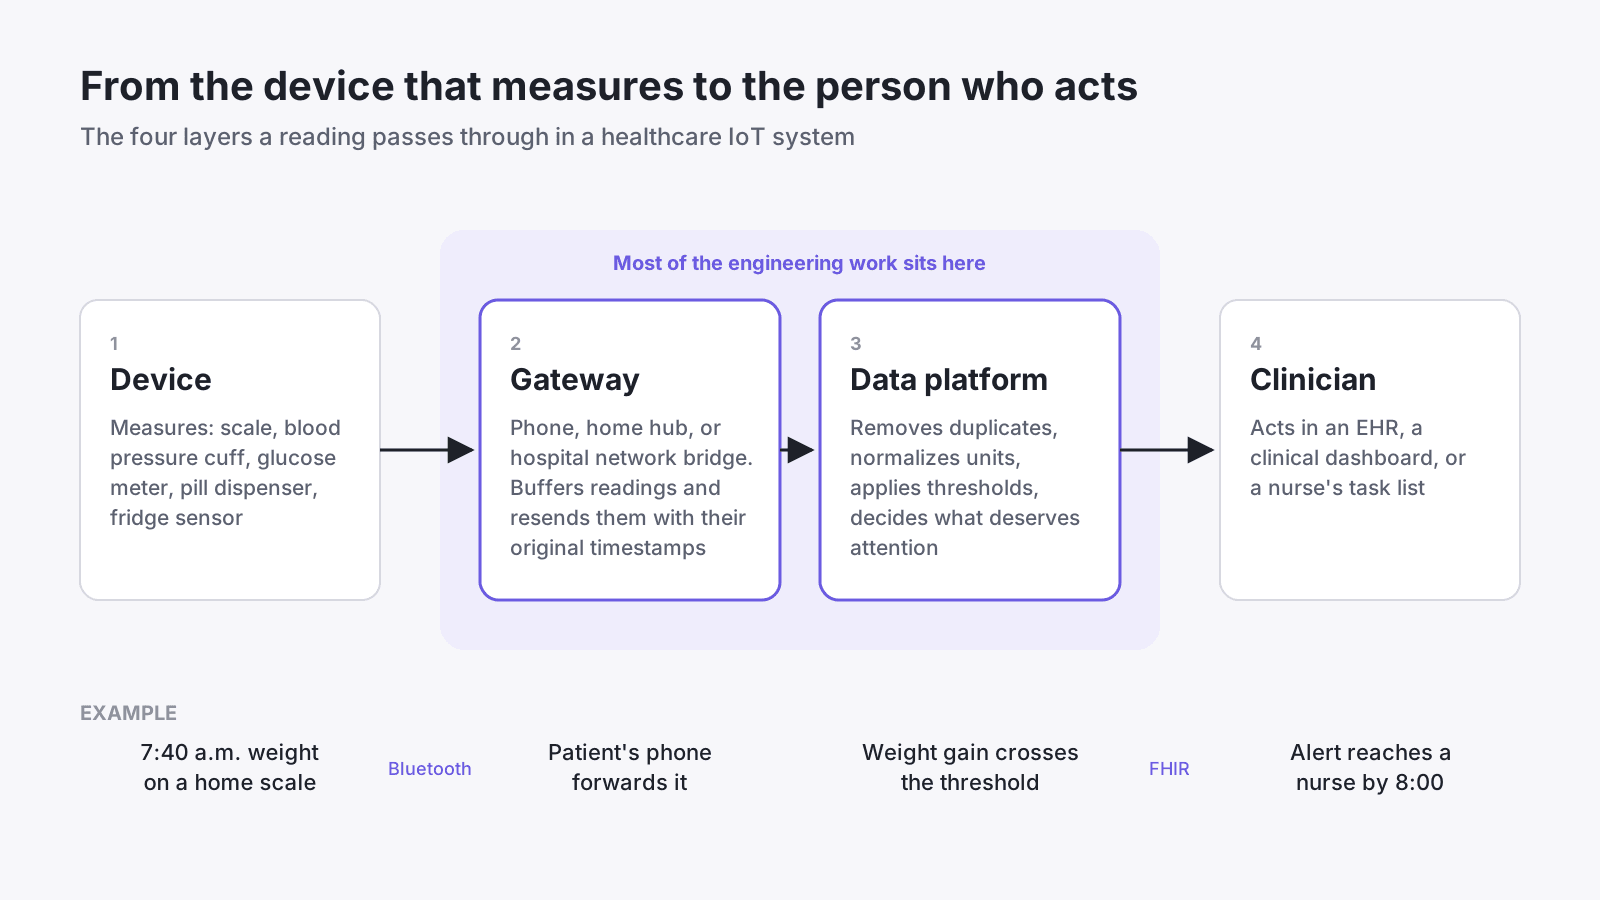
Devices at the first layer range from blood pressure cuffs and glucose meters to pill dispensers and vaccine-fridge sensors. Some are regulated IoT medical devices and others are consumer wearables, a difference that matters later for security and liability. Reporting rates range from one reading a day to several per second. That frequency drives almost every later decision, from battery life to storage cost to how alerts are grouped.
A gateway is usually the patient's phone, a home hub, or a hospital network bridge that forwards readings to the platform, often over Bluetooth. Phones lose signal and run out of battery, so a reliable design buffers readings locally and resends them with their original timestamps. Otherwise a clinician reviewing a trend sees readings in the order they arrived instead of the order they happened.
Next comes the data platform, which checks and stores what arrives and decides what deserves attention. Duplicates are removed here, units are normalized, and thresholds are applied. This layer is also where IoT healthcare solutions differ from each other, because two products built on the same device can behave very differently once the data lands. Most of the architecture decisions described later in this article are decisions about this layer.
At the last layer, a person acts in an EHR, a clinical dashboard, or a nurse's task list. In the United States, the common format for that handoff is FHIR. Its standards body, HL7, defines the Observation resource for measurements about a patient or device, including vital signs. Mapping readings to it early saves a rewrite when the first clinic asks for EHR integration.
Not every reading needs to arrive in real time. A daily weight can tolerate an hour's delay, while a fall detector cannot. Setting the acceptable delay per data type lets batch uploads handle most signals and keeps always-on connections for the few that need them.
What are the main IoT applications in healthcare?
The main IoT applications in healthcare are remote patient monitoring, hospital asset tracking, medication adherence, and wearable health data. Each creates its own data problem. Remote monitoring struggles with alert volume, hospitals with location accuracy, adherence programs with ambiguous events, and wearables with stream size. Choosing an application means choosing which problem to solve.
All four rest on the same foundation: device onboarding plus a data platform and an integration layer into clinical systems. Building that foundation once is cheaper than rebuilding it for each application. Our separate guide on digital transformation in healthcare software development covers how that foundation fits into the rest of a health system's software. For a first build, one device type and one integration is usually enough scope.
Remote patient monitoring and alert fatigue
Remote patient monitoring sends readings from home scales, blood pressure cuffs, and pulse oximeters to a care team that reviews them between visits. The evidence is real but moderate. A 2025 meta-analysis of 41 randomized trials and 16,312 patients, in a European Society of Cardiology journal, linked remote monitoring to lower mortality and fewer first heart failure hospitalizations.
Programs that added self-management and education modules did better still, a sign that the program around the device carries much of the result. A scientific statement published by the American College of Cardiology also notes that large trials of phone-transmitted weights and vital signs failed to show benefit.
Alert fatigue is the second problem. A review published by the American Association of Critical-Care Nurses found that 72 to 99 percent of clinical alarms are false. That range comes from hospital monitoring, but home programs share the mechanism, because a team flooded with meaningless alerts starts to miss real ones. A confirming second reading and a daily grouped review cut the noise without hiding a real change.
Volume is the quieter problem. One patient measuring blood pressure twice a day produces little data. A program with thousands of patients and several devices each produces a stream that people must review every day. Designing that review queue, more than the device connection, decides whether a remote monitoring program lasts. A cheap test before launch is to estimate daily review minutes per hundred patients.
Smart hospitals and asset tracking
Inside a hospital, IoT mostly tracks equipment and conditions rather than vital signs. Real-time location systems attach a tag to each infusion pump, wheelchair, or bed and report where it is, so staff stop searching corridors. Environmental sensors log fridge and room temperatures continuously instead of relying on a manual check twice a day.
Accuracy and meaning are the problem here, not volume. A location that says "third floor" helps little when a pump is needed in a particular room, and a tag that falls off makes an asset vanish from the map. The software should show how old each position is and flag tags that stop reporting. Linking equipment to maintenance records also keeps an overdue pump from being dispatched.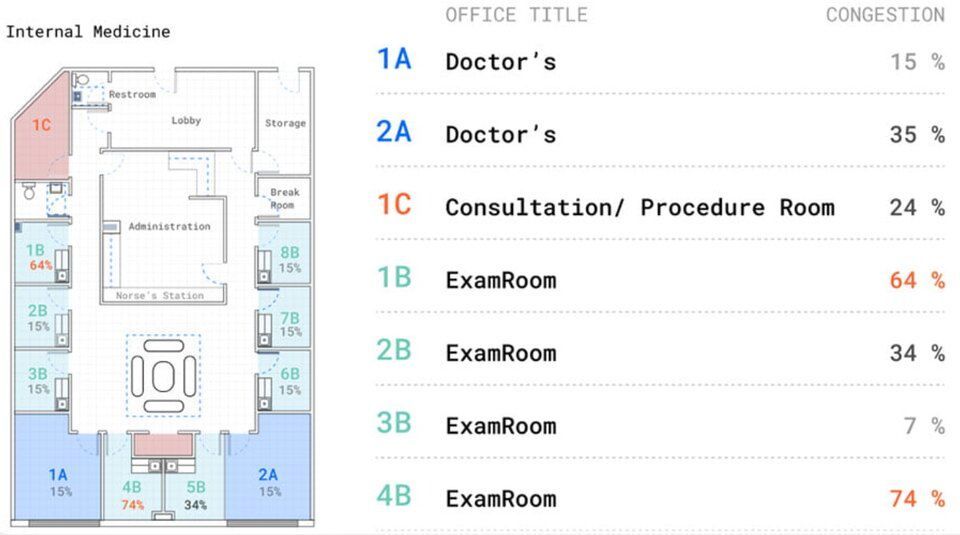
Medication adherence and event reliability
Adherence is a large, well-documented gap. A World Health Organization report found that adherence to long-term therapies in developed countries averages about 50 percent. Connected pill dispensers and smart caps record each dose and can alert a caregiver after a missed one.
A dispenser knows that a compartment opened, not that a pill was swallowed. Events can also arrive late when the device was offline. Reliable adherence data therefore needs device timestamps, a clear line between "opened" and "confirmed," and a rule for late events. Without them, caregivers get alarms about doses already taken, and after a week of false alarms they stop reading the alerts.
Wearables and the size of personal health data
Smartwatches and continuous glucose monitors produce far more data than the other applications. A heart rate sensor can report every few seconds for months. Patients value that history, but no clinician wants thousands of raw readings in a chart. The real question is how to shrink the stream without losing what matters clinically.
Most wearables are consumer products rather than regulated medical devices, and their accuracy varies by device and by activity. That affects how their data should appear in a clinical record. Marking the source device on every summary lets a clinician judge how much weight each number deserves, especially when consumer and regulated readings sit side by side. Consumer wearable data rarely belongs in an alert rule.
The table below compares the four applications by the data each produces, the standard it usually integrates through, and the measure that shows whether it works. Agree on that last column during planning. Without it, an application tends to be judged by how many devices are connected instead of by what changed for patients or staff.
Application | Data type | Integration standard | Outcome measure |
| Remote patient monitoring | Intermittent vitals: weight, blood pressure, oxygen saturation, glucose | FHIR Observation (Vital Signs profile), IEEE 11073 device data | Heart failure hospitalizations, time from reading to clinician review |
| Smart hospitals and asset tracking | Location updates, equipment status, fridge and room temperature | RTLS vendor APIs, FHIR Device and Location | Time to locate equipment, utilization, temperature excursions |
| Medication adherence | Dose events: compartment opened, dose confirmed, dose missed | FHIR MedicationStatement | Share of doses taken on schedule |
| Wearables and personal health data | Continuous streams: heart rate, activity, sleep, glucose | FHIR Observation summaries over a time period, with raw data kept outside the record | Data completeness, trend change over weeks |
What does IoT data do to your data architecture?
IoT data changes an architecture by adding continuous, high-volume, often incomplete streams to systems designed for occasional human entries. The response is to separate raw storage from the clinical record, summarize before anything reaches a clinician, and treat missing data as information rather than silence.
Raw data storage is the first decision. Raw readings belong in inexpensive, append-only storage, kept for audit and later analysis, while the clinical record receives summaries such as a daily average or a weekly trend. In FHIR terms, one summary can be a single Observation whose effective period covers the day, linked to the device that produced it. Clinicians then see the day, and engineers keep the seconds.
Gaps come second. Devices lose signal, batteries die, and patients take wearables off to charge them. A week with four days of readings is not a normal week, yet a chart of averages makes the two look alike. Every summary should carry a completeness figure, and FHIR includes a field for recording why an expected value is missing. A night without oxygen readings must never display as a normal night.
Ingestion capacity is the third decision. A device that reconnects after two days offline may upload everything at once, and a firmware bug can make one device send the same reading hundreds of times. Queue incoming data, deduplicate on device ID and timestamp, and cap what each device may send per minute, so one faulty unit cannot slow the system for every patient.
Device identity looks small in a demo. A cuff lent to one patient comes back, gets cleaned, and goes to the next one. The platform needs a registry of which device belonged to which patient and when, or readings land in the wrong record. FHIR's Device resource gives that registry a standard shape. Record each swap as a dated event rather than an edit to the patient's profile.
Alert logic can run on the device or on the platform. Rules on the device respond fast but are hard to change once shipped. Platform rules can be tuned per patient and audited, and each change leaves a record of who made it. That makes the platform the safer home for clinical alerts. Keep the rule set small enough for a clinician to review.
The last decision is what the clinician sees, and we treat it as a data question. In the clinical workspaces we build, vitals sit beside lab results and their reference ranges, and every read and write against the record is logged. Device summaries belong in that same view, with source and completeness attached. Our data visualization work follows one rule: every chart is a query result that carries its provenance.
A prototype hides all of this. With ten test devices, raw readings fit anywhere, gaps are rare, and someone reads every alert. A working demo proves the pipeline connects from end to end. It does not prove the design survives hundreds of patients, a week of dropped connections, and a care team with fixed review time each day. That is the load to design for.
How do HIPAA and security apply to IoT device data?
HIPAA covers IoT device data when a healthcare provider, health plan, or their business associate creates, receives, or stores it. Device data outside that relationship falls under other rules, mainly the FTC Health Breach Notification Rule. Connected medical devices also carry FDA cybersecurity requirements before they reach the market.
That line shapes the architecture. The HHS Office for Civil Rights publishes app scenarios that explain when a developer acts as a business associate, which usually means handling data on a provider's behalf. In that case, the build needs encryption, role-based access, audit logs, and breach procedures. A signed business associate agreement comes before any real patient reading enters an environment. Settling this late usually reopens the data model.
A wearable company selling directly to consumers is usually outside HIPAA, but not outside regulation. The Federal Trade Commission's amended Health Breach Notification Rule, effective July 29, 2024, applies to health apps and connected devices that HIPAA does not cover. A breach of that data requires notice to users and the FTC, and sometimes to the media. Device makers need a breach plan even without a clinic customer.
Manufacturers face a third layer. Since March 29, 2023, section 524B of the Federal Food, Drug, and Cosmetic Act has required cybersecurity information in premarket submissions for what the law calls cyber devices. The Food and Drug Administration publishes guidance on what that covers, including a software bill of materials. A team building the platform around a regulated device should expect to supply parts of it.
Device data needs the same controls as any clinical data, plus a few of its own. Each device should authenticate with its own credentials, so one compromised unit can be revoked without touching the rest. Firmware updates should be signed, and a device that stops reporting should raise a flag instead of quietly disappearing from the dashboard.
On our healthcare projects, we apply two defaults that carry over directly to device data. Development runs against anonymized data. Production access is limited to named engineers on the project, logged, and revoked when the engagement ends. Patient data stays in infrastructure the client controls, in the region its regulator requires, which for IoT includes the raw data store.
Consent works better per data stream than per app. A patient may share weight with a cardiology team but not sleep data, or pause a wearable during a hospital stay. Record each consent with its scope and the exact wording the patient saw. Then filter at ingestion rather than at display, so withdrawn data never enters the record in the first place.
Frequently asked questions


What is IoT in healthcare?
IoT in healthcare is the use of connected devices and sensors that send health or operational data to software platforms and clinical systems. It covers home monitoring and hospital asset tracking as well as medication adherence and personal health data. The devices collect readings, and the software decides which ones reach a clinician.


What are examples of IoT in healthcare?
What are the benefits of IoT in healthcare?
How does HIPAA apply to IoT device data?
How does IoT data integrate with an EHR?
How much does an IoT healthcare build cost?
What is the difference between IoT and RPM?


Author
With more than 10 years in full-stack development and real-world experience in healthcare, I bring a unique blend of technical skills and domain knowledge to every project. My focus is on building solutions that solve real problems and support better outcomes.
I often bring AI into the mix to enhance performance and simplify the complex. It’s all about creating smarter tools that help people work more efficiently and make better decisions.


Our Best Insights
Browse More Articles
Want to know what’s trending in the tech world? Our articles break it all down - quickly and clearly.
 Time to read: 11 min


Healthcare

Artificial Intelligence
November 4th, 2024
Machine Learning in Healthcare: Benefits, Use Cases, and Limits
Where machine learning helps in healthcare, why so many projects stall after the pilot, and when a simple rule beats a model.


 Time to read: 5 min
Healthcare
October 3rd, 2024
Digital Transformation in Healthcare: What It Means in Software Terms
From clinics to enterprise systems, digital transformation is making healthcare software more accessible, efficient, and patient-focused.


Thinking about building your own app?
Let's make it happen! Dream big, build smart - we’ll take care of the tech.
 Get a free consultation
We would like to load Google Tag Manager, which brings Google Analytics and a Google Ads audience tag with it, and Microsoft Clarity, which records how pages are used (clicks, scrolling, mouse movement) so that we can see where the site is hard to use. None of that is needed for the site to work, so it only loads if you agree, and you can change your mind at any time from the footer. Separately, Cloudflare measures this site's own performance without cookies and without identifying you; that runs either way and is explained in our Privacy Policy.